
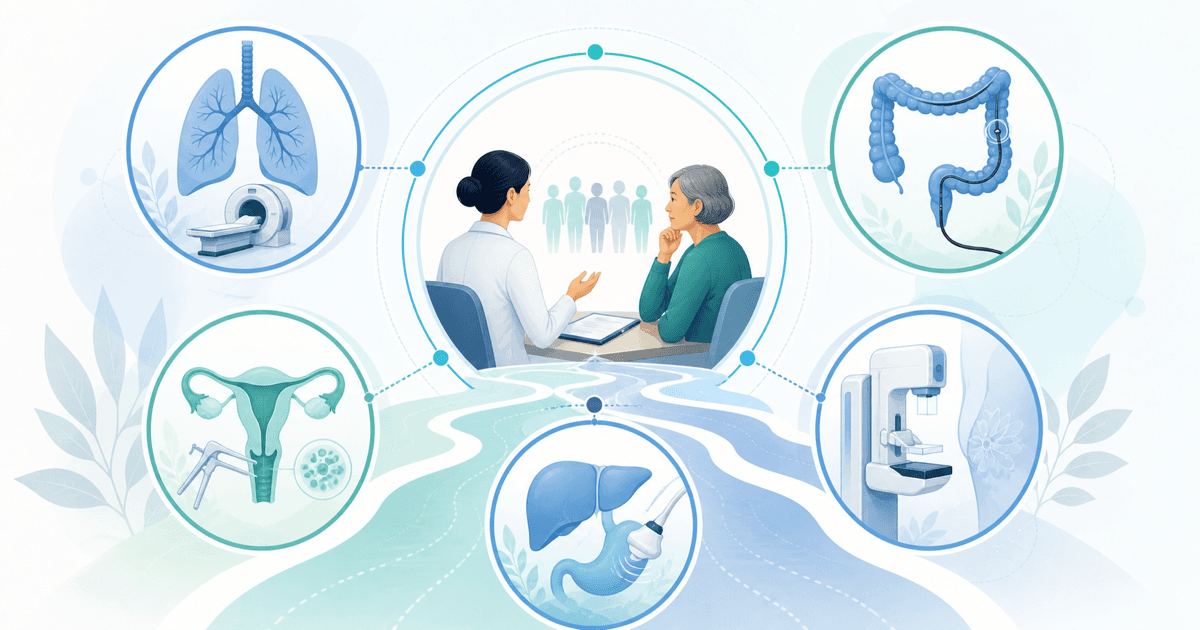
There is no universal cancer screening package
Screening is intended for people without related symptoms. Decisions depend on age, sex, smoking, family history, and past findings. Local medical guidance also matters. Screening may find some cancers earlier. It can also cause false results, overdiagnosis, and procedure-related harm.
Use these five topics to start a discussion. They are not a checklist for every adult.
1. Low-dose chest CT for people at high risk
Low-dose CT is used for people who meet defined lung-cancer risk criteria. The USPSTF recommends annual screening for some adults aged 50 through 80. They need at least a 20 pack-year smoking history. They must currently smoke or have quit within 15 years. Other countries may use different thresholds.
Important limits include:
- a routine chest X-ray cannot replace a low-dose CT screening program;
- “low dose” still involves radiation and can find noncancerous nodules;
- people outside high-risk groups should not arrange repeated scans for reassurance;
- anyone who smokes should also receive help to quit.
2. Colorectal cancer screening
Options include stool tests, colonoscopy, CT colonography, and other methods. Preparation, timing, accuracy, and risks differ. The USPSTF recommends screening average-risk adults from ages 45 through 75. Decisions from 76 through 85 depend on past screening and overall health.
Past polyps, bowel disease, hereditary syndromes, or strong family history may require earlier screening. Blood in stool, lasting bowel changes, or unexplained anemia need diagnostic assessment.
3. Cervical cancer screening
Cervical screening may use HPV testing, cytology, or both. Age and timing depend on local guidance, past results, immune status, and cervical surgery.
HPV vaccination lowers the risk of HPV-related cancers. It usually does not remove screening needs. An abnormal result does not mean cancer. Follow-up may include repeat testing, colposcopy, or biopsy.
4. Breast cancer screening
Mammography is a common breast screening method. Starting age and timing vary between guidelines. Some gene variants, young family diagnoses, or past chest radiation may change screening. Ask whether genetic counseling or earlier imaging is appropriate.
A new lump, bloody discharge, skin dimpling, or lasting one-sided change needs assessment. Do not wait for the next screening round.
5. Risk-based stomach and liver assessment
Gastroscopy and liver ultrasound are not routine tests for every adult. Local guidance may recommend surveillance for certain higher-risk people. Risks include H. pylori, family history, precancerous stomach changes, hepatitis B, or cirrhosis.
Blood tumor markers cannot prove that cancer is present or absent. Large marker panels can cause unnecessary follow-up and worry. Use them only for a defined medical question.
Preparing for a useful screening discussion
Bring earlier reports. List close relatives with cancer, smoking exposure, liver disease, and past polyps. Include any abnormal cytology. Tell the clinician about current symptoms. This helps separate:
- routine screening for average risk;
- earlier or more frequent surveillance for high risk;
- diagnostic care for symptoms or an abnormal result;
- tests with little expected benefit.
Our health screening service can help organize risks and past records. Already have abnormal imaging, pathology, or another result? Review the relevant oncology care pathway instead.
This article provides general education, not a personal testing plan. Follow local guidance and decide with a qualified clinician.