
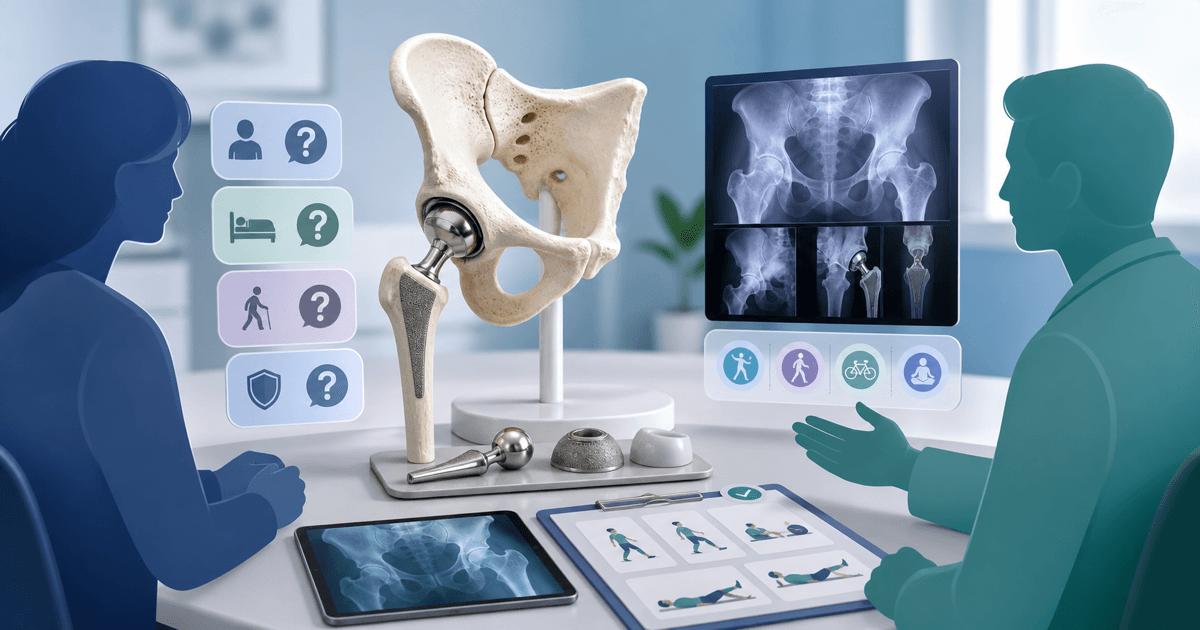
1. When is hip replacement considered?
Hip replacement may help when joint damage causes lasting pain and limited movement. Doctors usually consider it after nonsurgical care no longer provides enough relief. Common reasons include advanced arthritis, osteonecrosis, and certain fractures.
One X-ray or pain score cannot decide surgery. A doctor reviews symptom duration, walking, sleep, imaging, health, and personal goals.
2. What is the difference between total and partial replacement?
A total replacement replaces the femoral head and hip socket surface. A partial replacement mainly replaces the femoral side. It is often used for certain femoral-neck fractures in older adults. Choice depends on diagnosis, age, activity, bone quality, and socket condition.
3. How long do surgery and hospital care take?
Surgery time and hospital stay vary. Complexity, anesthesia, health conditions, and local recovery rules all matter. AAOS notes that some patients stay one or two days. Some selected patients leave on surgery day. Safe movement, pain control, and home support guide discharge.
4. How painful is recovery?
Pain, soreness, and swelling are expected after surgery. The care team usually combines several pain treatments. The goal is manageable pain for rest and rehabilitation. Sudden severe pain, fever, or wound drainage needs prompt medical advice.
5. How long can an artificial hip last?
Implant life depends on materials, fixation, weight, activity, infection, and anatomy. NHS information says many hip replacements last at least 15 years. No fixed lifespan can be promised. Younger patients should discuss possible revision surgery later.
6. When can I walk and resume daily life?
Many patients start walking with support soon after surgery. Before discharge, you should move safely and understand home exercises. Recovery can take several months.
NHS guidance says some people resume driving after at least six weeks. A clinician must confirm that driving is safe. Follow-up often occurs about 6 to 12 weeks after surgery. These are guides, not personal deadlines.
7. Which movements should be avoided?
Precautions depend on the surgical approach and your surgeon's instructions. Some patients avoid deep bending, crossed legs, low seats, or sudden twisting. Restrictions vary between operations.
Follow your discharge instructions, not an online checklist. Use a firm, higher chair when advised. Remove loose rugs and other trip hazards. Arrange early help from family or a caregiver.
8. Can I exercise after hip replacement?
After medical clearance, many patients choose walking, swimming, or stationary cycling. Running, jumping, contact sports, and fall-risk activities may load the joint more. Discuss them with your surgeon.
Walking does not replace prescribed rehabilitation. Continue the strength and mobility program from your rehabilitation team.
9. How should cost and insurance be estimated?
Costs depend on the hospital, implant, complexity, stay length, and rehabilitation. Complications may add costs. Insurance rules differ by country and plan.
Request a case-specific quote. It should list the implant, surgery, hospital care, tests, rehabilitation, and exclusions. Review our joint replacement cost and travel guide.
10. Which symptoms require urgent advice?
Follow your discharge instructions. Seek prompt help for increasing redness, drainage, fever, or sudden severe pain. New major leg swelling also needs urgent advice. Call emergency services for chest pain or trouble breathing.
Comparing hospitals or surgery plans? Review our orthopedic and joint replacement services. Bring hip imaging, past treatment records, and a complete health-condition list.
This article provides general education, not a surgical recommendation. Surgery, implant choice, and precautions require an orthopedic assessment.